Tesamorelin's abdominal target
Abdominal means a location, a diagnosis and a treatment history. Each changes the request.
Fat around organs and fat under skin
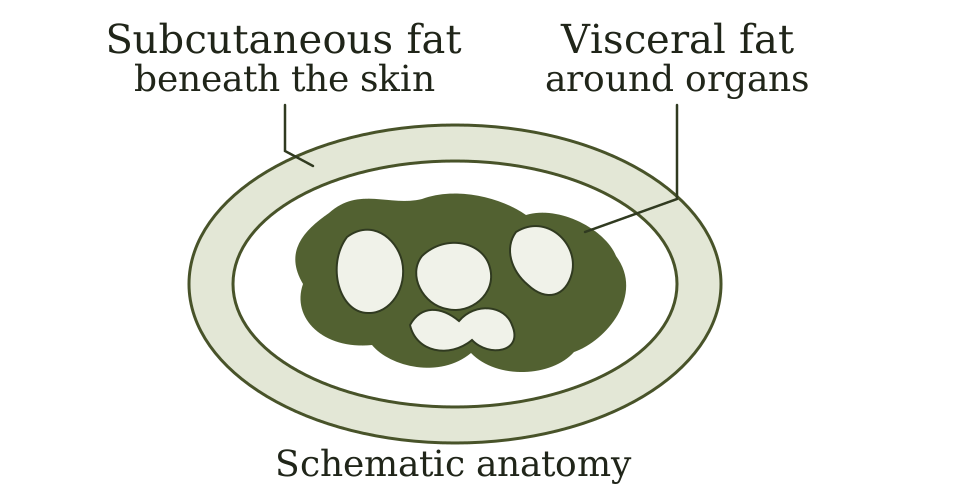
The abdominal fat targeted in tesamorelin trials is visceral adipose tissue, packed around the internal organs. Subcutaneous fat lies beneath the skin. Those compartments share a region of the body, while their location and behaviour differ. The pooled trials in HIV-associated lipodystrophy concern a particular disturbance of fat distribution in a particular population.
I retired the shorthand ‘belly-fat treatment’ once it began hiding the diagnosis. It invites a cosmetic picture of the abdomen and leaves out the diagnosis. Tesamorelin's US approval dates to 2010 and concerns excess abdominal fat in adults with HIV-associated lipodystrophy. Other uses remain off-label and investigational.
Abdominal and hepatic fat measurements
The JAMA trial of visceral and liver fat enrolled 50 antiretroviral-treated adults with HIV and abdominal fat accumulation: 28 assigned tesamorelin and 22 placebo. Over six months, the treatment effect on visceral fat was -42 cm2 (P=0.005), with a net fall of 2.9 percentage points in hepatic lipid-to-water percentage (P=0.003).
A 2026 meta-analysis of five randomised trials in HIV-associated lipodystrophy reported visceral adipose tissue down by a mean of 27.71 cm2 (95% CI -38.37 to -17.06; P<0.001), trunk fat down by 1.18 kg, hepatic fat fraction down by 4.28 percentage points and lean body mass up by 1.42 kg; all these outcomes had P<0.001.
I value the separate outcomes here: fat location, liver fat and lean mass each add something to the request. The people enrolled still define where these results apply; large randomised trials have not established the same benefit for general fat loss in people without HIV.
Tesamorelin withdrawal
In the 52-week tesamorelin programme, visceral-fat reduction was sustained at -18% over 52 weeks (P<0.001 versus baseline). Visceral fat reaccumulated after discontinuation. Glucose-parameter changes over the full follow-up were not clinically significant.
For me, the return of fat changes the conversation more than another efficacy adjective could. A request for a lasting alteration in body composition needs to include what maintaining that alteration would involve. The trial offers a year of observation and an account of withdrawal. Longer-term expectations need a longer-term record.
Pituitary stimulation and IGF-1
Tesamorelin is a stabilised analogue of growth hormone-releasing hormone. It stimulates the pituitary to release the body's own growth hormone in pulses; growth hormone then stimulates liver production of IGF-1, a growth factor.
The short mechanistic study in 13 healthy men is useful precisely because it asked an endocrine question. Over two weeks, mean overnight growth hormone increased by 0.5 ug/L (P=0.004) and IGF-1 by 181 ug/L (P<0.0001). Neither fasting glucose (P=0.93) nor insulin-stimulated glucose uptake (P=0.61) changed significantly. Those are hormone and glucose findings in healthy men, rather than evidence of abdominal-fat benefit for that group.
I like this use of the body's own hormone rhythm. The plausible uses still need their own trials. Raising a growth factor also brings a safety question into the room.
Tesamorelin safety
Active malignancy is a labelled contraindication. Long-term oncological safety data are limited, even though the trials reported no excess malignancy signal over 52 weeks. Modest glucose disturbances can occur, so a history of dysglycaemia matters alongside the glucose findings over the 52-week programme.
The LiverTox tesamorelin monograph assigns likelihood score E—unlikely to cause clinically apparent liver injury—and records no attributable liver-injury cases or new serum-enzyme elevations in the trials. The five-trial meta-analysis reported no serious adverse events. These are reassuring observations within the studies' populations and follow-up, and the growth-factor question stays on the agenda.
Tesamorelin is prohibited in sport under WADA category S2, in and out of competition. Research-grade material lacks the purity and potency oversight of the approved product.